Check list photo for ROI article

Yes, another checklist for your summer planning session. This stuff matters. A lot! Get it together, along with last week’s checklists, and you will be a top-value practice owner.

Essential/Critical Items

  • Proper, Written Associate and Employee Contracts
  • Premises Lease, Renewal and Assignment Options
  • Bank-Approved Professional Appraisal
  • Professional Incorporation and Minute Book Compliance
  • Clinical Services and Procedures Analysis
  • Active Patient Count, Complete with Demographics
  • Performance Data by Practitioner, per Hour/Day/Month
  • Accounts Receivable: Fully Reconciled and Purified

HOW DO I GET STARTED?

  • Assemble a team of professionals who have dealt with numerous optometric practice transitions.
  • Understand when and why each transition item should be introduced during the selling process. There is a strategic path to follow to ensure the integrity of your goodwill is maintained at all times.
  • Every transition is unique. Your broker will help you understand the many other transition items that will be added to your customized checklist.
  • Your ROI Broker will provide a transition manual explaining the dozens of minor business issues that will be transferred to the new owner and guide you through the many steps in the process, such as how, what and when to tell staff and patients.

 

Jackie Joachim

JACKIE JOACHIM

Jackie Joachim graduated from the University of Toronto with a Bachelor of Arts degree in Economics and Political Science and has close to 30 years of experience in the health care sector. She began her career in banking where she learned how to finance health care practices. With 10 years of experience in practice management, she developed and delivered seminars to healthcare professionals across the country, coached hundreds of practitioners for planning, marketing, patient education, human resources and financial management. She has been a keynote speaker at both national and provincial association conventions where she has had the privilege of speaking with thousands of health care professionals across Canada.  You can reach at  Jackie.joachim@roicorp.com or 1-844-764-2020.


Share:
Rate:

0 / 5. 0

Jade Bodzasy Pivot to Patience July-August 2026

When a child arrives for pre-testing already in a state of “high alert”, whether it’s a full-blown tantrum, silent freezing, or vibrating with anxiety, the clinical data usually becomes secondary to emotional regulation. If you try to force a measurement now, the “noise” from their stress will likely yield inaccurate results anyway.

Here is how to apply EQ to de-escalate the situation and salvage the appointment.

  1. The “Neutrality” Reset

When a child is elevated, the environment often becomes high-decibel and high-stress. As the professional, your first move is to introduce Neutrality.

  • Lower the Volume: Speak at a volume just above a whisper. This forces the child to quiet down to hear you and breaks the cycle of “shouting over” the noise.
  • Minimize the Audience: If the pre-test room is crowded or visible to the waiting area, close the door or move to a quieter corner. Reducing sensory input is the fastest way to lower cortisol.
  1. Narrative Labeling (The “I See You” Technique)

High EQ doesn’t mean “fixing” the emotion; it means acknowledging it. Children often escalate because they feel misunderstood or out of control.

  • Acknowledge the Feeling: Instead of saying “Don’t be scared,” try: “It looks like you’re feeling really overwhelmed right now. This room has a lot of big machines and that can be a lot for anyone. What should we do to help your body calm down?”
  • Give Permission: Tell them it is okay to be nervous. By removing the pressure to “be brave,” you often remove the resistance.
  1. Tactical Agency: Give Them the “Off” Switch

Anxiety is rooted in a lack of control. To get the data you need, you have to give some power back to the child.

  • The “Stop” Signal: Give them a physical signal (like raising a hand) that means you will stop the test immediately. When they know they have an “exit,” they are far more likely to stay in the chair.
  • The Choice Illusion: Ask, “Do you want to do the ‘balloon machine’ (autorefractor) first, or should we take the ‘eyeball picture’ (fundus photo)?” The order doesn’t matter to your data, but it matters immensely to their sense of autonomy.
  1. Utilization of “Collaborators”

In these moments, the parent is your most important Collaborator.

  • Indirectly regulate the Parent: If the parent is frustrated or embarrassed by the child’s behavior, it will escalate the child. Calmly tell the child, so that the parent can hear: “It’s okay, lots of people feel this way about this space. Let’s just give you a minute to calm your body. Maybe your parent could help show you how the chin rest works?”
  • Physical Grounding: If the child is small, have them sit on the parent’s lap for the pre-testing. The physical proximity to their “safe person” can calm them down enough to get a good reading.
  1. The “Pivot” Strategy

Sometimes, the EQ move is knowing when to stop. If you have tried de-escalation for five minutes and the child is still in a “fight or flight” state, pushing forward will only create a traumatic association with eye care.

  • Reschedule with Intent: Pivot the conversation. “I can see today is a big day for your eyes. Why don’t we try one small thing, and then we’ll save the rest for another visit when you’re feeling more like a scientist?”
  • The “Win” Ending: Always end on a successful note, even if it’s just the child successfully sitting in the chair for five seconds. Give the sticker anyway. You are “playing the long game” for their future eye health.


Summary for the Team

When a child is elevated, your job title shifts from Technician to Regulator. By focusing on their emotional safety first, you aren’t “wasting time”, you are ensuring that when you finally do get that measurement, it is accurate, and the patient is willing to come back next year.

Want to learn more about Emotional Intelligence, find more resources at www.emotionalintelligenceconsultinginc.com


Jade Bodzasy

Jade Bodzasy

Jade Bodzasy, Founder of Emotional Intelligence Consulting Inc., is a dedicated Coach and Consultant for Optometric Practices. Her extensive background includes over 20,000 hours of expertise focused on customer relations, work structure refinement, training method development, and fostering improved work culture within Optometric practices.

Certified in Rational Emotive Behavior Techniques (REBT), Jade possesses a unique skillset that empowers individuals to gain profound insights into the origins of their behaviors, as well as those of others. Leveraging her certification, she equips optometry practices with invaluable resources and expert guidance to establish and sustain a positive, healthful, and productive work environment.


Share:
Rate:

0 / 5. 0

Diana Monea Children The Hidden Treasure

Practitioners who focus on pediatric eye care can drive lasting practice growth by prioritizing children’s vision, treating children as an essential yet often overlooked source of continuity, personal achievement, and gratification.

Vision is vital for a child’s development and education. About 80% of learning is visual, so even minor vision issues can hinder school performance and self-esteem. Teachers frequently request vision checks when students struggle, showing the importance of eye care in learning.

Lessons from the Real World

Over 50 years, my team and I managed three Eye Health Centres. A constant lesson we have learned is that children build practices. When children trust us, families return. Parents value their child’s care, which creates relationships over generations. Pediatric care gives lasting practice growth through relationships, unlike short-term marketing. Each appointment is a chance to teach families about the importance of eye health, and educating parents is key. Many people do not know that vision cannot be replaced at any price and that hidden eye issues, not obvious to the parent or child, can affect learning and confidence. Explaining vision’s role in a child’s development helps parents see the value of a comprehensive eye health exam.

Discussing with parents the impact of vision and the role genetics plays also increases engagement and adult referrals. When parents see eye health as essential to their child’s development and understand that vision changes as a child grows, they become long-term and consistent advocates for routine care. Educating families about the benefits of regular eye care not only benefits children but also practices by deepening trust and creating lasting loyalty. Soon, annual exams become part of a continuous health care plan for life.

Connecting Through Clear Direct Communication

Proper communication is essential when addressing children. It is important to communicate directly with children using simple terms. Effective pediatric communication means engaging children in their own treatment, not just addressing the parents. For example, instead of “We need to patch the eye,” say, “We cover your stronger eye, so the weaker one gets stronger. Do you see this eye doesn’t see as well?” Even young kids understand simple explanations. When they know why treatment matters, they feel less anxious and have fun in making their “broken” eye see better. Such engagement boosts cooperation.

You may then ask children about their favourite colour, advising the optician in front of the child about the colour and asking to see the child when they have selected the glasses. Such interaction increases child compliance and impresses parents, which builds positive rapport – everyone wants to come back because they are treated “special.”  When children and even adults feel noticed, they cooperate and eagerly want to come back.

These instances build practice success. Happy children make the experience positive and encourage trust. When kids enjoy the clinic, parents return, improving retention and reputation.

The clinic environment matters. A friendly environment turns routine care into memorable visits. Positive experiences encourage children to follow treatment, improving results and trust.

Children who grow up receiving consistent eye care often return as adults and bring their own children. This cycle strengthens the foundation of practice, creating enduring relationships over the course of decades.

Later, practitioners will see that generational continuity is a key factor in succession planning through “goodwill.” Word-of-mouth referrals from satisfied families remain the most powerful and cost-effective form of practice growth. Pediatric eye care is about forming lasting trust and relationships. Prioritizing children’s care is the central catalyst for sustainable, generational growth in practice.

Children are not only patients but also the essential treasure of practice builders, directly shaping lives and guaranteeing the success and longevity of eye care practices.


Dr. Diana Mae Monea, OD, FAAO, MHRM

Dr. Diana M. Monea, OD

Dr. Diana M. Monea is an award-winning optometrist, author, and keynote speaker with more than four decades of leadership in clinical practice, business ownership, and professional education. Founder and former CEO of Eye Health Centres, she now focuses on consulting, mentorship, patient care, and public speaking.


Share:
Rate:

0 / 5. 0

Roxanne Arnal ECBC Understanding Capital Gains Inclusion Rates, the LCGE, and Capital Losses

For many optometrists, much of their financial planning focuses on practice growth, long-term investing, and retirement preparation. Yet some of the most significant tax consequences arise when an investment, business asset, or practice interest is sold.

Understanding how capital gains, capital losses, and available exemptions are treated can provide valuable context when making major financial decisions.

What Is a Capital Gain?

A capital gain occurs when an asset is sold for more than its adjusted cost base. Common examples include investments held in a non-registered account, real estate that is not a principal residence, or shares of a private corporation, such as your practice.

For example, if an investment was purchased for $100,000 and later sold for $150,000, the capital gain would be $50,000.

Unlike employment or professional income, only a portion of a capital gain is taxable.

Understanding the Capital Gains Inclusion Rate

As of 2026, the capital gains inclusion rate remains at 50%.

This means that only half of a realized capital gain is included in taxable income. Using the previous example, a $50,000 gain would result in $25,000 of taxable income.

While the inclusion rate has changed several times throughout Canadian tax history, capital gains continue to receive preferential tax treatment compared to employment or professional income.

Why Capital Gains Matter for Optometrists

An optometrist may realize capital gains through:

  • The sale of shares of an incorporated practice
  • The sale of investments held outside registered accounts
  • The transfer of certain business assets
  • The disposition of recreational or investment real estate

Since practice value often represents a significant portion of an optometrist’s net worth, understanding the tax implications of a future sale becomes increasingly important as retirement approaches.

The Lifetime Capital Gains Exemption (LCGE)

One of the most valuable tax provisions available to Canadian business owners is the Lifetime Capital Gains Exemption (LCGE).

The LCGE allows eligible individuals to shelter a significant portion of capital gains realized on the sale of qualified small business corporation shares. The exemption was increased to $1.25 million, with the limit indexed to inflation beginning in 2026.

When available, the LCGE can significantly reduce or even eliminate tax on a portion of the gain realized on the sale of a professional corporation.

However, eligibility requirements are detailed and must be satisfied both at the time of sale and throughout the 24 months leading up to the transaction.

Key tests must be met regarding:

  • The nature of the corporation’s assets
  • The ownership of the shares
  • The active business use of corporate assets

Seemingly minor issues, such as excess passive investments and permanent life insurance policies accumulating inside a corporation, can sometimes affect eligibility. As a result, corporate structures should be reviewed well before a planned sale to preserve eligibility for the exemption.

What Happens When Investments Decline? Understanding Capital Losses

Not every investment produces a gain.

When an asset is sold for less than its adjusted cost base, the resulting loss is known as a capital loss.

Capital losses generally cannot be used to reduce employment income, professional income, or other ordinary sources of earnings, but rather are applied against taxable capital gains.

This creates several planning opportunities.

A capital loss may be used to:

  • Offset taxable capital gains realized in the current year
  • Carry back against taxable capital gains from any of the previous three taxation years
  • Carry forward indefinitely to offset future taxable capital gains

This flexibility can be valuable during periods of market volatility, particularly when gains and losses exist across different holdings.

Looking Beyond the Tax Result

Although tax considerations are important, they are only one part of a larger financial picture that may include retirement planning, liquidity needs, risk management, and estate objectives.

Tax on a capital gain is often the result of a successful investment outcome.

Conversely, realizing a loss solely for tax reasons may not improve long-term financial results if the investment strategy itself no longer aligns with broader objectives.

For optometrists who already have significant exposure to a single business asset through their practice, this balanced perspective can be particularly valuable. The tax treatment of gains and losses matters, but so does maintaining an investment portfolio that supports diversification and long-term financial stability.

A Useful Framework

Capital gains rules influence investment decisions, business succession planning, and retirement outcomes throughout an optometrist’s career.

The inclusion rate determines how gains are taxed, the LCGE may provide significant relief on the sale of qualifying practice shares, and capital losses can help offset gains when investment results are uneven.

Understanding how these rules work provides a stronger foundation for making informed financial decisions over time.

Have more questions? We’re here to help.

Roxanne Arnal is a Certified Financial Planner®, Chartered Life Underwriter®, Certified Health Insurance Specialist, former optometrist, Professional Corporation President, and practice owner. She is dedicated to empowering individuals and their wealth by helping them make smart financial decisions that bring more joy to their lives.

This article is for information purposes only and is not a replacement for personalized financial planning. Errors and omissions excepted.


ROXANNE ARNAL,

Optometrist and Certified Financial Planner

Roxanne Arnal graduated from UW School of Optometry in 1995 and is a past-president of the Alberta Association of Optometrists (AAO) and the Canadian Association of Optometry Students (CAOS). She subsequently built a thriving optometric practice in rural Alberta.

Roxanne took the decision in 2012 to leave optometry and become a financial planning professional. She now focuses on providing services to Optometrists with a plan to parlay her unique expertise to help optometric practices and their families across the country meet their goals through astute financial planning and decision making.


Share:
Rate:

5 / 5. 1

Maryam Moharib AI in Eye Care Six Tools Influencing Clinical Practice- 2026

Artificial intelligence (AI) has been widely discussed in recent years, but its impact on Canadian eye care is now tangible. From personalized dry eye management to automated retinal screening and advanced OCT biomarker analysis, AI-driven platforms are helping clinics improve efficiency, standardize documentation, and strengthen diagnostic support.

Not all AI tools serve the same function. Some operate as screening and triage systems, others deliver quantitative imaging analytics, and some provide broader clinical decision-support resources.

Below is an overview of six AI-enabled tools currently shaping clinical conversations in Canadian eye care.


  1. CSI Dry Eye Software – Standardizing Dry Eye Care

Dry eye disease remains one of the most common conditions encountered in primary eye care. CSI Dry Eye Software is a cloud-based clinical management platform designed to structure and streamline dry eye assessment and management.

Using AI-driven algorithms, the platform synthesizes patient questionnaires, diagnostic testing, and clinical findings. It identifies likely contributing mechanisms—such as evaporative or aqueous-deficient components—and generates structured, individualized treatment plans.

Key capabilities include:

  • Analysis of multiple dry eye tests, patient questionnaires, and clinical data to identify underlying causes and contributing factors.
  • Support for personalized, protocol-driven treatment plans by comparing patient data against databases of OTC products, prescription therapies, and in-office procedures.
  • Longitudinal tracking of patient progress across multiple visits.
  • Cloud-based access (SaaS) with structured dashboards, automated reminders, customized reporting, and follow-up tools to streamline workflow.
  • Reduced chair time and decreased subjective variability through standardized analysis and treatment guidance.

Integration considerations: CSI operates as a browser-based SaaS platform and does not require proprietary hardware. It works with most dry eye data already collected in clinic. EMR integration varies by system; summaries can typically be exported or incorporated into records.

Best suited for: Clinics seeking structured, protocol-driven dry eye management.


  1. OphtAI – Automated Retinal Screening

OphtAI is designed for automated analysis of colour fundus photography. It screens for diabetic retinopathy, glaucoma, and age-related macular degeneration (AMD), generating real-time reports with lesion mapping, severity grading, and confidence scoring.

Key features include:

  • Detection of major retinal diseases from fundus photographs.
  • Real-time analysis with downloadable PDF reports detailing lesion mapping and severity grading.
  • Flexible access via web portal, mobile application, or API.
  • Designed for rapid, automated screening in tele-ophthalmology or population-based programs.

Integration considerations: The platform is accessible via web, mobile, or API. In Canada, it is also currently integrated with Tecksoft EyeVu EMR. It does not require proprietary imaging hardware beyond a compatible fundus camera.

Best suited for: Primary care environments and large-scale screening programs.


  1. Altris AI – OCT Biomarker Quantification

Altris AI focuses on AI-enhanced interpretation of OCT scans. The platform detects and quantifies more than 70 retinal pathologies and biomarkers, including drusen subtypes, fluid, atrophy, and edema. It is particularly positioned for monitoring AMD, in both dry and neovascular forms.

Core features include:

  • Automated detection and quantification of 70+ retinal biomarkers and pathologies.
  • Highlighting and longitudinal tracking of AMD-related features to support monitoring of progression and treatment response.
  • Conversion of raw OCT data into structured, reproducible outputs, including heatmaps, Early Treatment Diabetic Retinopathy Study (ETDRS) grid visualizations, graphs, and quantitative measurements.
  • Support for research workflows through longitudinal comparisons and advanced analytics.

Integration considerations: Altris AI offers cloud-based access as standard, with on-premise options available. It is vendor-neutral and designed to integrate into existing OCT workflows, compatible with devices from multiple major manufacturers.

Best suited for: Retina-focused practices and imaging centres requiring detailed OCT analytics.


  1. AI4Eyes – Ocular Surface Test Consolidation

AI4Eyes is a Canadian-developed platform that combines proprietary hardware with AI-driven diagnostic software. The tool consolidates approximately 10 anterior segment tests into a streamlined, AI-guided imaging workflow. Clinicians receive AI-supported diagnostic suggestions and treatment recommendations for review.

Notable capabilities:

  • Consolidation of multiple anterior segment tests into a single AI-guided workflow.
  • Machine learning–based analysis of ocular surface parameters.
  • Personalized treatment suggestions that clinicians can validate and refine.

Integration considerations: AI4Eyes integrates into the pre-test workflow and supplements existing diagnostic data collection. Unlike pure SaaS platforms, it requires acquisition of dedicated hardware.

Best suited for: Practices investing in integrated anterior segment and dry eye diagnostics.


  1. VisualDx – Broad Clinical Decision Support

VisualDx is a clinical decision-support platform rather than a dedicated eyecare AI tool. It contains a database of more than 45,000 medical images and peer-reviewed clinical content.

Clinicians can input signs and symptoms to generate differential diagnoses—particularly valuable when ocular findings intersect with dermatologic or systemic disease.

Core benefits include:

  • Searchable content extending beyond ophthalmology, supporting multi-system evaluation.
  • Access to treatment guidance, ICD coding support, and complication alerts.
  • Patient education tools to facilitate communication and shared decision-making.

Integration considerations: VisualDx is web-based and accessible via browser or app, with API integration options available.

Best suited for: Clinicians managing complex or multi-system presentations.


  1. OCTolyzer – Open-Source OCT Research

OCTolyzer occupies a distinct niche as an open-source OCT analysis toolkit developed for research use. In Canada, it may be used in research environments but is not intended for direct patient diagnosis.

The platform performs automated retinal and choroidal segmentation and extracts quantitative metrics such as thickness measurements and vascular indices.

Integration considerations: OCTolyzer runs on standard computing systems and is platform-agnostic. It is not a regulated clinical diagnostic device and is intended for academic research, validation studies, and AI development.

Best suited for: Universities, research laboratories, and AI development teams.


In Summary

AI adoption in Canadian eye care continues to accelerate, with tools serving diverse clinical objectives:

  • CSI Dry Eye Software and AI4Eyes focus on structured ocular surface management.
  • OphtAI supports retinal screening.
  • Altris AI enhances OCT biomarker analysis.
  • VisualDx strengthens cross-disciplinary differential diagnosis.
  • OCTolyzer advances academic research and innovation.

Selecting the appropriate platform depends on clinical focus, practice size, patient volume, regulatory considerations, and readiness to integrate new technologies into established workflows. As AI continues to evolve, its role in Canadian optometry is shifting from experimental to operational—reshaping how optometrists assess, document, and manage ocular disease.


Maryam Moharib

Maryam Moharib, BOptom, BHSc, CSPO, CAPM

Maryam holds degrees in Health Sciences from the University of Ottawa and in Optometry from Anglia Ruskin University in Cambridge, England. She has dedicated many years to working alongside ophthalmologists in refractive surgical clinics, where she gained significant experience in clinical training and in EMR implementation for various software platforms.

Maryam has also worked as a certified product owner with an EMR software company where she played a key role in effectively bridging the gap between clinical needs and technology. Additionally, her certification in project management from the Project Management Institute has equipped her with the skills to lead implementation and transformative clinic projects successfully.


Share:
Rate:

0 / 5. 0

Roxanne Arnal Debt Free, Cash Free Deals in an Optometry Practice Sale July 2026

When an optometry practice changes hands, attention often settles on the purchase price. But beneath that number is a more practical question: what exactly is being transferred to the buyer, and what remains with the seller?

A “debt free, cash free” deal is one way this is addressed, particularly when equipment financing, leases, inventory, and working capital are involved. The phrase sounds simple, but the details can materially affect what the buyer receives and what the seller keeps.

What does “debt free, cash free” mean?

At its core, this structure separates the operating value of the practice from its financing history. The buyer acquires the clinic, patient base, goodwill, systems, and operating assets, but not the seller’s excess cash or debt obligations.

For optometry practices, this distinction matters because equipment loans and leases are often tied directly to the assets needed to run the clinic. Exam lanes, imaging systems, diagnostic technology, and optical equipment may all carry financing that must be dealt with before closing.

Equipment loans and the reality of settlement

Equipment loans are often paid out before closing so the buyer receives the equipment free and clear. That keeps the transaction clean, but it also affects the seller’s net proceeds.

A practice may have a strong headline value, yet the owner’s actual outcome can be reduced if recent technology purchases still carry significant debt. This is one reason sellers need to look beyond the sale price and understand how financing will be settled.

When are leases transferable?

Leases introduce a more nuanced layer. Unlike term loans, some equipment leases can be assigned to a buyer, subject to lender approval. When this happens, the obligation may travel with the asset rather than being paid out beforehand.

In practice, there are three common ways to address leases:

  • Assigned to the buyer: the buyer assumes the remaining payments, usually with lender approval and a purchase price adjustment.
  • Paid out by the seller: the seller clears the lease before closing so the asset transfers free and clear.
  • Handled through a negotiated adjustment: the economics of the lease are reflected in the deal rather than strictly assigned or paid out.

The important detail is that “transferable” does not mean “automatic.” Lease terms, lender policies, and buyer qualifications all matter. This should be clarified early in the transaction process to avoid last-minute disruption.

Working capital and inventory

Even in a debt free, cash free deal, the buyer expects to receive a clinic that can operate on day one. That usually means a normal level of working capital, including receivables, payables, prepaid expenses, and inventory.

Most transactions establish a working capital target that reflects what is typical for that practice. If the seller runs inventory unusually low before closing, or builds it up beyond normal levels, the purchase price may be adjusted back to the agreed baseline.

Inventory deserves particular attention in an optometry practice because frames, lenses, and contact lenses support both patient care and revenue generation. It is usually included as part of working capital delivered at closing, but it is not always valued at retail.

  • Inventory is typically measured at cost rather than retail value.
  • Slow-moving frames, outdated styles, or discontinued product lines may be discounted or excluded.
  • Unusual changes before closing are often adjusted back to a normal operating level.

For sellers, this can highlight capital tied up in product. For buyers, it helps ensure the clinic remains ready to operate immediately after closing.

The definitions drive the outcome

The phrase “debt free, cash free” provides structure, but the definitions drive the outcome. Which debts must be cleared? Which leases can be assigned? What level of working capital is normal? How will inventory be valued?

These details directly influence both the buyer’s experience and the seller’s net result. In optometry, where equipment investment and inventory management are part of daily practice life, clarity on these points can prevent surprises and create cleaner expectations on both sides.

Have more questions? We’re here to help.

Roxanne Arnal is a Certified Financial Planner®, Chartered Life Underwriter®, Certified Health Insurance Specialist, former optometrist, Professional Corporation President, and practice owner. She is dedicated to empowering individuals and their wealth by helping them make smart financial decisions that bring more joy to their lives.

This article is for information purposes only and is not a replacement for personalized financial planning. Errors and omissions excepted.

ROXANNE ARNAL,

Optometrist and Certified Financial Planner

Roxanne Arnal graduated from UW School of Optometry in 1995 and is a past-president of the Alberta Association of Optometrists (AAO) and the Canadian Association of Optometry Students (CAOS). She subsequently built a thriving optometric practice in rural Alberta.

Roxanne took the decision in 2012 to leave optometry and become a financial planning professional. She now focuses on providing services to Optometrists with a plan to parlay her unique expertise to help optometric practices and their families across the country meet their goals through astute financial planning and decision making.


Share:
Rate:

0 / 5. 0

Trevor Miranda Hearing and Vision clinic article image

If eyes are the windows into the soul, perhaps ears are the doorway to the heart. Both vision and hearing play huge roles in enjoying life. Whether it is the ability to read or the ability to participate in conversations, both are central to day-to-day connection and independence. Like vision, hearing deteriorates with age. Early detection and timely intervention can improve long-term vision and hearing health and overall wellness.

One Stop for Vision and Hearing Care

At three of our five clinics at Cowichan Eyecare, we have integrated hearing services. My brother is a Doctor of Audiology and leads our hearing care division.

Our first instinct was to operate in a silo and simply share space. Some of that may have stemmed from a fear of being viewed as nepotistic if we more closely integrated the vision and hearing offerings. Over time, we have continued to integrate both services in a more intentional way, and patient feedback has been overwhelmingly positive. The convenience of addressing hearing needs in a place you already trust for eyecare, or vice versa, has quelled our initial reservations about joint care.

There are also real economies of scale that create efficiency and cost savings with hearing and vision integration. We share a front desk and a call-answering system, which streamlines communication and scheduling. We use a common Practice Management System (PMS) for billing and recalls, which helps us keep patients on track with follow-up care. Shared restrooms and lunchrooms allow for efficient use of space, leaving more room for special testing or retail areas in the clinic.

One of the key differences between vision and hearing is that there is often a significant lag between the onset of hearing loss and the time a patient seeks corrective help. Increasing awareness in both disciplines, and cross-educating our teams, is a practical way to reduce that lag and get people the support they need sooner. In our experience, simply having both services under one roof creates more natural conversations about overall sensory health.

The Role of Hearing and Vision on Cognition

Hearing is inextricably linked to cognition. Audiologists often say the ears collect sound, but it is the brain that hears. There is substantial research highlighting a connection between untreated hearing loss and cognitive disorders. More recent research is also showing that improving hearing can reduce the risk of cognitive decline. Keeping our hearing healthy is an important part of keeping our brain in an optimal state.

Because we cannot fully close our ears the way we can close our eyes, the brain is constantly receiving and processing sound. This ongoing processing keeps the auditory centres of the brain engaged and “exercised.” When we hear, the brain chooses to pay attention to some sounds (for example, conversation) and to tune out others (for example, the hum of traffic). That filtering is work, and it is part of what makes hearing such an active, brain-driven process.

We all have a certain amount of cognitive capacity, or “brain power.” That resource is limited, and the amount we have available at any given time depends on many factors, including fatigue. When we have untreated hearing loss, we use cognitive resources, and often our vision as well, to fill in the blanks of what our ears are not giving us. In conversation, hearing is the first step before we can understand content. A hearing deficiency demands cognitive resources first, and whatever brain power is left over can then be used to process, remember, recall, think ahead, draw analogies, create and understand jokes, and stay engaged in the moment.

Research has shown a significantly higher incidence of cognitive disorder in people with untreated hearing loss. For example, individuals with hearing loss between the ages of 45 and 65 have been shown to have two to five times the risk of reduced cognition and dementia, depending on the severity of the hearing loss (Lin et al., 2011; Livingston et al., 2020). More recent research is beginning to show that when hearing loss is treated, cognitive performance can improve significantly (Jiang et al., 2023).

The primary advantage of correcting milder degrees of hearing loss may be the potential cognitive benefit. When missing sounds are filled in with assistive devices such as hearing aids, it reduces demand on limited cognitive resources. Those resources can then be deployed for higher-order tasks, including comprehension, memory, and social connection. In cases where vision is compromised such as macular degeneration optimizing hearing is even more important due to limited cognitive resource theory.

The Business Opportunity

Our metrics show that hearing care revenue represents about 30% of the eyecare revenue opportunity. That means that, with little added space, a significant additional source of revenue can be available in many eyecare clinic settings. A hearing booth is required, but the footprint is manageable and the impact can be meaningful. A hearing booth is simply a small, sound-treated room that allows accurate testing and fittings in a quiet environment. There are few eyecare subspecialties that can provide this amount of financial upside without major renovation.

Of course, the details matter. The revenue-sharing agreement needs to be worked out, and medical manpower needs to be accounted for, including appropriate compensation for the audiologist. When it is structured properly, the integration can be both clinically valuable and financially sensible.

Wearables as the Gateway

New eyeglasses are coming to market that will be hearing-assistive. These glasses will provide sound enhancement and refinement by cancelling noise and using directional microphones built into the frame. These hearing glasses will likely provide solutions sooner for patients with low to moderate hearing loss.

They will not replace customized hearing instruments, and they are not meant to. Still, as an entry point, hearing glasses can be assistive at a lower cost, while also delivering great vision with prescription lenses. For some patients, that may reduce barriers and normalize getting help earlier.

The Focus on Wellness

Optometry and eyecare will continue to evolve. Technological advancements in wearables, enhanced diagnostics, and individualized solutions will allow ECPs to support better overall health and wellness for our patients. Can you hear it? The future will be clear, and it sounds amazing!

If you have noticed the TV volume creeping up, or you find yourself asking people to repeat themselves more often, bring it up at your next eye exam. We can help you understand what is normal, what is not, and what the next step could be.

2024 Trevor Miranda

DR. TREVOR MIRANDA

Dr. Miranda is a partner in a multi-doctor, five-location practice on Vancouver Island.

He is a strong advocate for true Independent Optometry.

As a serial entrepreneur, Trevor is constantly testing different patient care and business models at his various locations. Many of these have turned out to be quite successful, to the point where many of his colleagues have adopted them into their own practices. His latest project is the Optometry Unleashed podcast.


Share:
Rate:

0 / 5. 0

Roxanne When Does the Cost Match the Risk June 2026

Most optometrists make risk decisions every day without labelling them as such. Insurance decisions are rarely about absolutes. They are about trade-offs. Which risks are worth transferring and which are better carried?

With summer vacations being on everyone’s mind, travel bookings are a good example. The choice between a non‑refundable rate and a fully refundable one is something we have all contemplated.

The Scenario

A recent search for an August weekend in Banff illustrates this well. The promotional, non‑refundable rate came in at $834. The fully refundable option was $950.

That decision point offers a useful lens for thinking about insurance more broadly, particularly when the stakes move from discretionary spending to income protection.

Putting a Price on Flexibility

The $116 upcharge represents roughly 14% of the base room rate.

In effect, the hotel is offering insurance against a specific risk: the possibility that plans change. Illness, weather, family needs, or simple timing conflicts could make the trip impractical. Paying more converts uncertainty into flexibility.

Many travelers accept this trade‑off without hesitation. The dollar amount is known, the risk is easy to understand, and the downside of losing the full $834 feels tangible and uncomfortable.

What about the Alternative?

The loss being insured is finite. If for some reason you don’t get to Banff, you have lost out on your pre-paid rate of $834. The financial impact is contained. Nevertheless most of us will still be irritated by “throwing that money away”, despite the fact that it’s not likely to alter our long‑term financial plans.

Still, the market price for that certainty is clear: about 14%. And you may be willing to throw away the $116 in case you do have to cancel.

Scaling the Same Logic to Income

Now consider a very different risk.

Imagine you earn about $160,000 of self-employed income. How much do you and your family depend on your ability to earn this income? What would happen if you suddenly found yourself not just unable to attend your Banff vacation, but you actually land in the hospital because you’ve become seriously injured or ill? It won’t just take away your August weekend but takes you out of your work for six months or more.

NOTE: this income equates to about $100,000 of after tax annual insurable benefit.

What’s the Cost?

This is not an extreme scenario. Statistics Canada data consistently show that working Canadians face a one in three probability of disability lasting longer than 90 days during their careers, with a smaller but very real subset experiencing long‑term or permanent impairment.

Applying the same 14% “insurance cost” logic used in the hotel example produces a striking comparison.

Fourteen percent of a $100,000 annual benefit is $14,000 per year.

Most optometrists would immediately recognize this as far higher, up to 4x higher, than typical disability insurance premiums for that level of coverage, even with robust definitions and long benefit periods.

Why the Comparison Feels Uncomfortable

The discomfort isn’t mathematical. It’s behavioural.

We are generally more willing to pay a visible premium to protect a known, short‑term expense than to commit to ongoing premiums for a lower overall‑claim probability, high‑impact risk, even when the latter carries far greater financial consequence.

A cancelled trip is easy to picture. A long-term disability is abstract, emotionally distant, and uncomfortable to contemplate. As a result, the value of the insurance protecting against it is often discounted, even when the pricing is far more favourable on a proportional basis.

In the Banff example, the insurer (the hotel) is charging 14% to protect a few days of discretionary spending. In the disability example, insurers often charge a much smaller percentage of about 3% of the insured benefit to protect a decade or more of core income.

Risk You Can Absorb vs. Risk You Can’t

This contrast highlights an important distinction: not all risks deserve the same treatment.

Many optometrists can comfortably absorb the loss of an $834 hotel room. Cash flow may be dented, but life goes on. The loss does not compound, and it does not threaten future earning capacity.

Income loss from disability is different. It affects not only spending, but savings, debt servicing, practice viability, and long‑term independence. It is also difficult to self‑insure without very substantial capital already in place.

From a proportionality standpoint, disability insurance is often protecting something far more critical at a lower relative cost than many everyday “insurance‑like” decisions.

The Quiet Role of Behavioural Comfort

This isn’t an argument against refundable hotel rooms. Comfort has value, and certainty can be worth paying for, particularly when plans involve family or limited travel windows.

Rather, the comparison invites reflection. Many routinely pay double‑digit percentages to insure modest, temporary risks, while hesitating over single‑digit percentages to insure the asset that underpins everything else: your ability to earn.

That gap often has less to do with economics and more to do with what feels immediate and relatable.

A Proportional Way to Think About Insurance

Looking at insurance decisions through a proportional lens can bring clarity:

  • How large is the potential loss?
  • How long would the impact last?
  • What percentage of the protected value am I paying to transfer the risk?

When framed this way, the question shifts from “Is this premium expensive?” to “Is this risk one I can realistically afford to assume?”

For many optometrists, the answer differs sharply between cancelled travel plans and prolonged loss of income.

A Grounded Takeaway

The Banff hotel example is not about travel. It’s about perspective.

When a 14% upcharge to protect a weekend getaway feels reasonable, it creates a useful benchmark for evaluating how we price certainty elsewhere in our financial lives. Disability insurance, viewed through the same proportional lens, often reveals itself not as costly protection, but as comparatively efficient risk transfer.

And that realization tends to come not from fear, but from calmly comparing what we insure, how much we pay, and what truly matters if plans don’t go as expected.

Have more questions? We’re here to help.

Roxanne Arnal is a Certified Financial Planner®, Chartered Life Underwriter®, Certified Health Insurance Specialist, former Optometrist, Professional Corporation President, and practice owner. She is dedicated to empowering individuals and their wealth by helping them make smart financial decisions that bring more joy to their lives.

This article is for information purposes only and is not a replacement for personalized financial planning. Errors and Omissions exempt.

ROXANNE ARNAL,

Optometrist and Certified Financial Planner

Roxanne Arnal graduated from UW School of Optometry in 1995 and is a past-president of the Alberta Association of Optometrists (AAO) and the Canadian Association of Optometry Students (CAOS). She subsequently built a thriving optometric practice in rural Alberta.

Roxanne took the decision in 2012 to leave optometry and become a financial planning professional. She now focuses on providing services to Optometrists with a plan to parlay her unique expertise to help optometric practices and their families across the country meet their goals through astute financial planning and decision making.


Share:
Rate:

0 / 5. 0

Diana Monea article AI and EMR Integrated into an Optometric Practice

Optometry has evolved from paper files to digital records, from phone calls to virtual communication, and in the future, perhaps even to robots (bots) assisting humans. Every day, innovation takes on a new dimension as artificial intelligence (AI) is integrated into electronic medical record (EMR) systems. The future of communication and diagnostics in eye care remains uncertain: will AI replace parts of what we do, or simply help us work more efficiently, more accurately, and at lower cost while improving the patient experience?

  1. AI Reduces Office Time, Improves Documentation, and Enhances the Patient Experience

AI can capture the doctor–patient conversation and generate clinical notes automatically. Unlike basic dictation tools, more advanced systems can organize information into the appropriate sections such as chief complaint, history, exam findings, assessment, and plan.

AI can also support tasks such as:

  • Billing and coding support
  • Documenting diagnostic impressions and recommended next steps

Used well, these tools can improve the patient–doctor experience. The clinician can stay more present with the patient, while reducing clerical workload and documentation interruptions. This can also help reduce clinician burnout by making charting more seamless and efficient at the point of care, reducing the need for after-hours documentation.

2. Integrating AI and EMR

When AI outputs can be structured and integrated into an optometry EMR, the system can help identify patterns and automate repetitive, but necessary, tasks. Depending on the platform and workflow, AI-enabled EMR integration may support:

  • Prescriptions and documentation support
  • Referrals and communication templates
  • Treatment plan tracking and management
  • Patient education materials based on clinical findings
  • Interpretation support and clinical prompts
  • Revenue cycle support
  • Analytics and reporting

With thoughtful integration, the EMR can begin to function less like a passive record and more like an active clinical assistant.

3. AI Imaging as Clinical Support

OCT, fundus photography, corneal topography, and visual field data can be analyzed using AI models trained on large datasets. Applications may include:

  • Diabetic retinopathy screening
  • Glaucoma risk and progression monitoring
  • AMD risk stratification and progression tracking
  • Corneal irregularity detection
  • Automated comparison of serial scans

AI-powered support tools may also combine imaging with clinical measurements such as intraocular pressure, pachymetry, and refraction. These tools are not a replacement for clinical judgment, but they can add a layer of insight and help flag subtle changes that are easy to miss in busy practice.

4. AI’s Impact on Practice Management

Administrative inefficiencies are a major source of stress and cost in many practices. AI-enabled systems can assist with:

  • Insurance claim submission, verification, and follow-up
  • Coding support, rejection handling, and resubmissions
  • Appointment scheduling, reminders, and recall workflows

By reducing errors and repetitive front-desk work, AI can free staff to focus on higher-value patient service and practice operations; helping reduce administrative burden and improve consistency.

5. Patient Communication

AI can improve patient understanding and satisfaction by:

  • Providing personalized summaries of findings
  • Explaining recommendations and outcomes in plain language
  • Generating visuals or simplified graphics that help patients understand their results
  • Supporting appointment booking and capturing patient concerns ahead of visits
  • Providing relevant pre-visit or post-visit information for recommended procedures

Practice bonus: when patients are better informed, they are often more confident and more compliant, leading to smoother visits, fewer misunderstandings, and a stronger overall experience for patients, staff, and clinicians.

6. Standardization Through AI and EMR Connectivity

A major advantage of AI is its potential to integrate with EMR systems more seamlessly than older workflows. Historically, many EMRs operated in silos, requiring manual entry and increasing the risk of transcription errors.

With tighter device-to-EMR integration, key data, such as refractions, visual acuities, intraocular pressure measurements, and imaging results, can populate charts automatically. This reduces redundancy, improves accuracy, and supports standardization across the clinical team.

7. The Advantage of an AI-Enhanced Practice

When documentation, scheduling, coding, and routine analysis are partially automated, optometrists gain time to do what matters most: be human. That means having more capacity to educate, reassure, and build trust without sacrificing the operational demands of modern practice.

The future of optometry will be shaped by clinicians who use AI strategically to enhance care, reduce burnout, and elevate the patient experience. Practices that adopt AI, and integrate it effectively into their EMR, will be better positioned to improve efficiency, strengthen resilience, and pursue clinical excellence in the face of tomorrow’s practice challenges.


Dr. Diana Mae Monea, OD, FAAO, MHRM

Dr. Diana M. Monea, OD

Dr. Diana M. Monea is an award-winning optometrist, author, and keynote speaker with more than four decades of leadership in clinical practice, business ownership, and professional education. Founder and former CEO of Eye Health Centres, she now focuses on consulting, mentorship, patient care, and public speaking.


Share:
Rate:

0 / 5. 0

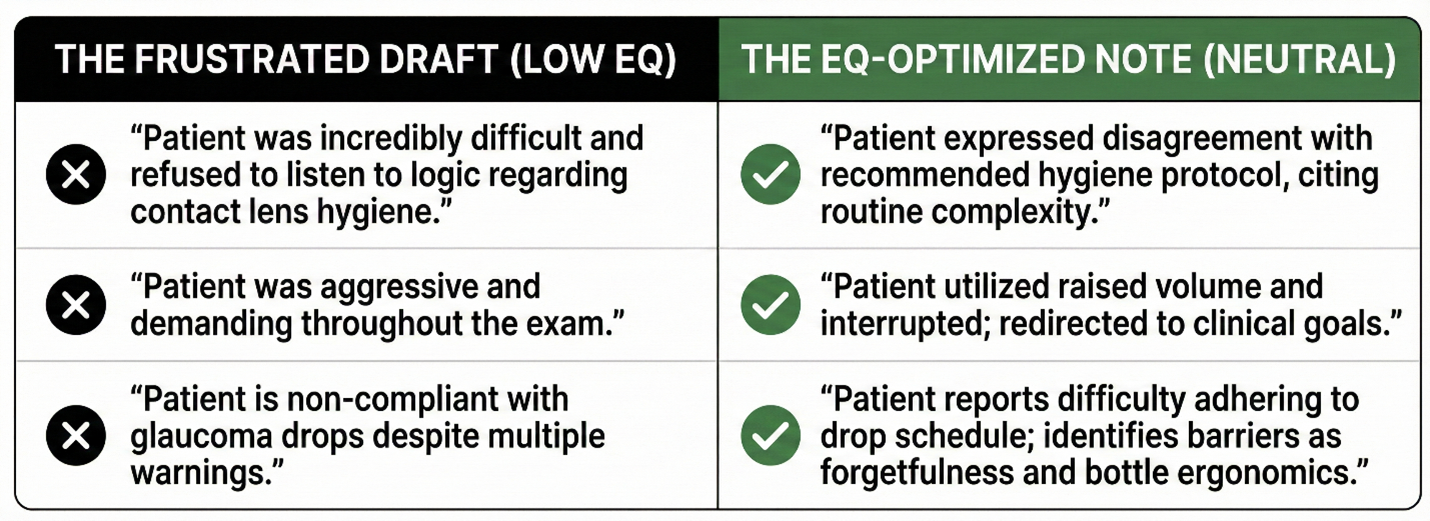
Jade Bodzasy article The Paper Trail of Frustration

You know that feeling. It’s the end of a grueling day of back-to-back refractions, and you’ve just finished with a particularly challenging patient. You sit down at your computer, exhausted and perhaps a bit annoyed. In that high-pressure moment, your Electronic Medical Record (EMR) often becomes an unintended outlet for your stress.

It is incredibly easy for your internal state, whether it’s frustration or pure exhaustion, to “leak” into your documentation. But we live in an era where patients have immediate legal access to every word you type. Because of this, your ability to pivot from an emotional reaction to a neutral, EQ-informed observation isn’t just a nice “soft skill”, it’s a professional necessity.

The Trap of “Emotional Leakage”

Emotional Intelligence (EQ) starts with your own self-awareness. In the context of note-writing, this means catching yourself when your current mood is steering your keyboard. When you’re frustrated, your notes tend to shift from objective observations to subjective judgments.

Keep an eye out for these “red flag” words that signal emotional leakage:

  • “Difficult”
  • “Uncooperative”
  • “Demanding”

These terms don’t actually provide clinical value; they just serve as a digital “vent.” The real danger is the Bias Echo. These labels can follow a patient indefinitely, creating a cycle where every technician or specialist who sees that chart next approaches the patient with the same preconceived frustration you felt.

The Legal Reality: Your Patient is Reading

The medical record has evolved. It’s no longer a private, “behind-the-scenes” dialogue between professionals; it is a shared document. Thanks to patient portals, your patients can—and do—read your notes.

Imagine a patient reading a note that characterizes their behavior as “aggressive” or “hostile.” If they were acting out because they were terrified of losing their vision or didn’t understand the procedure, reading those words can be traumatizing. Once that therapeutic alliance is fractured by a poorly worded note, the professional repercussions are real. A note written in a moment of pique can quickly become primary evidence of perceived bias.

Your New Skill: Neutral Reframing

The core EQ skill you need to master is Neutral Reframing. This is the process of taking the “raw data” of a frustrating interaction and stripping away the emotional adjectives to reveal the clinical facts. You aren’t omitting what happened; you are describing it with such objectivity that the behavior speaks for itself.

Restoring Relational Clarity

When you choose neutral language, you achieve Relational Clarity. You are documenting the truth of the encounter while protecting your professional integrity. Most importantly, you are leaving the door open for a successful interaction next time. A neutral note gives the next professional a baseline to solve the problem (like improving drop ergonomics) rather than just bracing themselves to manage a “difficult” person.

Documentation as a Human Skill

Your success in eye care is increasingly defined by your human skills. High-EQ record keeping is an act of discipline. It requires you to pause, acknowledge your own frustration, and choose a narrative that serves both the patient’s health and your own career longevity. Feelings are temporary, but the record is permanent.

Is Your Team Prepared for the “Open Notes” Era?

Mastering neutral, high-EQ record keeping is essential for protecting your practice and fostering patient trust. I help eye care professionals and team leaders build the relational clarity needed to thrive in high-pressure environments.

Learn more at: www.emotionalintelligenceconsultinginc.com


Jade Bodzasy

Jade Bodzasy

Jade Bodzasy, Founder of Emotional Intelligence Consulting Inc., is a dedicated Coach and Consultant for Optometric Practices. Her extensive background includes over 20,000 hours of expertise focused on customer relations, work structure refinement, training method development, and fostering improved work culture within Optometric practices.

Certified in Rational Emotive Behavior Techniques (REBT), Jade possesses a unique skillset that empowers individuals to gain profound insights into the origins of their behaviors, as well as those of others. Leveraging her certification, she equips optometry practices with invaluable resources and expert guidance to establish and sustain a positive, healthful, and productive work environment.


Share:
Rate:

0 / 5. 0